

Top Angiographic Control Syringes for Precision Contrast Delivery
2026-09-05
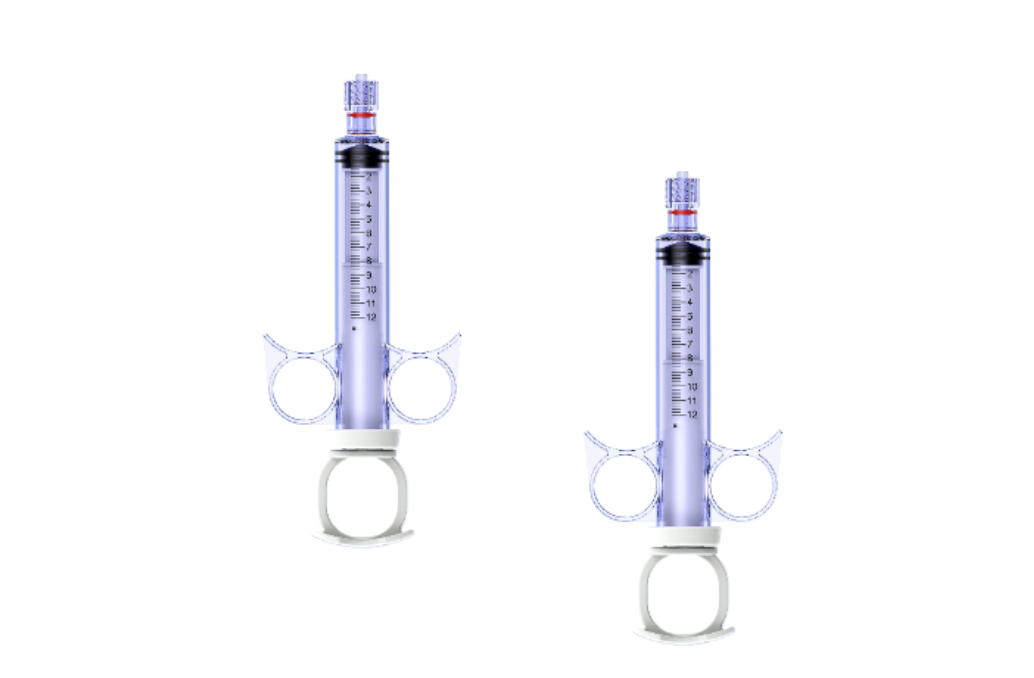
If you’ve ever watched contrast delivery lag behind your hand movement—or fought a syringe that fights back—you know that precision in angiography starts with the tool in your grip. That’s where INT enters the picture, designing angiographic control syringes around tactile feedback, clarity, and high-pressure reliability. Instead of treating the syringe as an afterthought, we’re looking at the options that give interventional teams the control they need when every milliliter counts.
When a Half-Milliliter Matters More Than You Think
Half a milliliter is roughly a tenth of a teaspoon, small enough to vanish into a sink drain. Yet in a syringe, that volume stops being trivial. A 0.5 mL slip in an insulin dose can crash blood sugar levels; in an epidural, it can blunt a contraction without fully relieving pain. Pharmacists and nurses treat that line on the barrel as a hard boundary, not a suggestion.
Outside medicine, the same half-milliliter quietly decides outcomes. Espresso shots drift from balanced to sour when the yield changes by that amount. A perfume formula loses its top notes if one component is off by a fraction. Even a child's liquid antibiotic becomes harder to mask when the dose creeps upward. The pattern is always the same: scale deceives, and the smallest measures often hold the tightest tolerances.
Dead Space Is Where Contrast Volume Goes to Hide
In a well-mixed circulatory model, iodinated contrast behaves predictably. But real vasculature is full of stagnant corners—aneurysm sacs, false lumens, atrial appendages, and tortuous venous segments—where flow nearly stops. These are the dead spaces, and they quietly siphon contrast out of the active circulation, holding it in pockets that opacity late and clear even later.
The result is a misleading enhancement pattern. A bolus that should peak sharply in the arterial phase gets blunted, because a portion of the injected volume never reaches the target territory on time. Instead, it lingers in those low-flow zones, creating a delayed, smeared washout that can mimic slow flow or poor cardiac output. Radiologists learn to recognize this phenomenon on dynamic scans: a vessel that stays dense long after its neighbors have faded is often not diseased—it’s just a dead space refusing to let go of the contrast.
Quantifying this hidden reservoir matters more than most realize. In CT perfusion or angiography, dead space volume can lower the effective dose delivered to organs, skewing time-density curves and making peak enhancement appear weaker than the injection actually was. Accounting for these stagnant compartments—whether through longer scan delays, saline chasers, or simply reading with suspicion—turns a frustrating artifact into a predictable variable.
Barrel Clarity After Cycle Number Fifty
By the time the fiftieth cycle completes, the liquid finally surrenders its last stubborn haze. Early on, each pass through the oak left behind a swirling murk of fine char dust and suspended esters, but those particles have long since settled into the staves or been filtered out by sheer repetition. What remains in the barrel now catches the light with an almost brittle transparency, the kind of clarity that makes you think of cold spring water rather than something dragged through char and time.
The shift isn’t just visual. That fifty-cycle mark is where the nose stops fighting itself—no more raw alcohol spike wrestling with wet wood. Instead, the aroma lifts cleanly: a bright line of vanilla pod, a faint drift of dried apricot, and underneath it all a mineral edge that only shows up when the spirit has stopped carrying sediment. You can hold the glass up to a window and see straight through to the other side, but there’s still a golden weight to it, a viscosity that clings to the glass longer than it should.
Most barrels never reach this point because people get impatient or the angels take too much. But at fifty, the clarity isn’t about filtration tricks or chill haze removal. It’s earned, cycle after cycle, until the barrel itself decides it has nothing left to cloud the spirit except its own memory.
Why a Smooth Plunger Is Not Always About Silicone
Silicone gets a lot of credit, but a smooth plunger often starts with the barrel it rides against. Even the softest silicone seal will drag across micro-ridges left by rough molding or machining. A polished glass, stainless, or coated plastic bore can remove more friction than swapping seal materials ever will.
The shape of the seal matters more than the material itself. A carefully designed lip or O-ring cross-section can flex and rebound without creating too much contact area. Too much contact makes even premium silicone feel sticky, while too little sacrifices consistency. That balance is what separates a clean draw from one that stutters on every pull.
Lubrication and maintenance tip the scale just as much. A dry silicone plunger in a dry barrel will always resist, no matter how soft the rubber feels. The same plunger with a light film of compatible grease, or paired with the right fluid viscosity, moves far more freely. Smoothness is a system trait, not a single ingredient.
Pressure Surprises During High-Flow Injections
In many high-flow injection setups, the pressure trace does not settle into the smooth curve that steady-state calculations suggest. Right after the pump ramps up, a sharp overshoot can appear even when the downstream path is wide open. This brief spike often gets dismissed as gauge noise, but it repeats run after run and can reach values well above the predicted line pressure.
A less obvious surprise occurs once flow has stabilized. If the fluid carries even a small amount of dissolved gas, the drop in local pressure at a restriction can release microbubbles that momentarily reduce density and increase velocity. The result is a fluctuating pressure signature that looks unstable but is actually a repeatable two-phase effect. Operators who swap in a larger line or open a bypass often see the fluctuation vanish, which points to geometry rather than a faulty sensor.
The practical takeaway is that high-flow behavior cannot be judged from low-flow data alone. Short-duration transients and gas breakout effects demand faster sampling and, in some cases, a small accumulator or a revised valve-opening sequence. Ignoring these pressure surprises usually leads to conservative operating limits that hide the real cause.
Cutting Prep Time Without a Second Pair of Hands
Most of the time, the kitchen slowdown isn't a lack of skill; it's the back-and-forth between fridge, cutting board, and sink. Start by grouping tasks before you touch a knife. Pull every vegetable, herb, and protein you need onto the counter at once, then wash and dry them in a single pass. When you peel or trim, do it over a large bowl or compost bin so scraps never force you to pause and walk away.
Rethink the order of cuts as well. Dense items like carrots and potatoes can be broken down first because they hold up, while delicate herbs or tomatoes should wait until the end so they don't turn to mush under other ingredients. If a recipe calls for both sliced and diced pieces of the same vegetable, do all the slicing first, set that portion aside, then adjust your grip for dicing. That small shift avoids constantly resetting your hand position and keeps a steady rhythm going.
A second set of hands is really just a stand-in for a few well-chosen tools and habits. Use a bench scraper to move piles from the board to the pan without spilling, keep a damp towel under the cutting board so it doesn't slide, and designate one bowl for finished prep. When everything lands in the same place, you spend less time hunting for the next ingredient and more time actually cooking.
FAQ
A precision control syringe typically has a low-resistance plunger, a locking Luer connection, and clear barrel markings. These features give the operator steady, one-handed control while watching live fluoroscopy without over- or under-injecting contrast.
Clear polycarbonate or similar materials let you spot air bubbles, blood reflux, or contrast volume at a glance. That immediate visual check reduces the chance of pushing air into a vessel.
Most teams prefer 10 to 12 mL syringes because they hold enough contrast for multiple test injections but stay light enough for fine manual control during long procedures.
They are mainly built for hand injection, but many have standard Luer fittings that can connect to manifold systems or extension tubing. For power injection, a dedicated high-pressure syringe is usually required.
Locking Luer hubs prevent accidental disconnection under pressure, and some designs include a rotating collar so the tubing can be positioned without twisting the catheter. Air-free priming is simplified by clear graduation lines and a smooth plunger.
No, these are single-use sterile devices. Reusing them can introduce bloodborne pathogens and compromises the plunger lubrication, which leads to jerky or imprecise delivery.
Low-friction silicone seals, ergonomic thumb rings, and a shorter barrel length reduce hand fatigue. A smooth, consistent stroke matters when you are trying to opacify small branches without injuring the vessel.
Yes. A secure Luer lock maintains a closed system, so pressure goes into the catheter instead of leaking at the hub. This gives consistent delivery and preserves the contrast volume you intend to inject.
Conclusion
Precision contrast delivery in angiography often hinges on details that never show up in basic spec sheets. A half-milliliter discrepancy can alter diagnostic clarity or vascular pressure more than many operators expect, which is why the top control syringes are engineered to hold exact volumes under real-world handling rather than just in a calibration lab. Dead space, for instance, quietly steals contrast at every connection point, and the best designs minimize that hidden reservoir so injected volume matches intended dose. After fifty autoclave cycles, barrel clarity becomes a trust issue: cheaper plastics cloud over, making it harder to spot microbubbles or residual contrast, while high-grade materials keep their transparency and dimensional stability. A smooth plunger feel isn't simply about heavy silicone coating—it's about tolerance matching between plunger and barrel, so glide remains consistent without stiction or free play, even during long procedures.
High-flow injections expose another layer of quality. Pressure surges can cause barrel expansion or connector leaks if the syringe wall isn't reinforced properly, and a surgeon may notice a subtle lag or jet inconsistency. The leading control syringes are built to handle transient pressure spikes without deforming, preserving both flow rate and tactile feedback. Finally, prep time matters when you're working without an extra pair of hands. Thoughtful features like wide finger flanges, clear graduation marks that resist wiping off, and luer locks that engage with a confident click allow a single operator to load, purge, and swap syringes quickly. These practical considerations separate a generic syringe from one truly suited for precision angiography, where every fraction of a milliliter and every second of prep can influence patient outcomes.
Contact Us
Contact Person: Jeffrey
Email: [email protected]
Tel/WhatsApp: 86-0633-2230056
Website: https://www.sd-intmedical.com

